


Persistent Depressive Disorder is a long-lasting depression that lasts at least two years in adults and one year in teens. Patel et al. (2024) reviewed the condition in “Persistent Depressive Disorder,” published by StatPearls. They define it as a depressed mood for most of the day, more days than not, over that period. It is characterized by a consistently low mood and various other symptoms that significantly impact daily functioning.
Common symptoms of PDD include persistent sadness, fatigue, low self-esteem, difficulty concentrating, changes in appetite, and sleep disturbances. While these symptoms are not as severe as those of major depression, their long-lasting nature leads to considerable distress.
Healthcare professionals diagnose PDD through clinical interviews, self-report questionnaires, and standardized diagnostic criteria, such as those outlined in the DSM-5. A thorough assessment helps differentiate PDD from other mood disorders.
The causes of PDD involve genetic predispositions, biochemical imbalances in the brain, and environmental factors such as prolonged stress or traumatic experiences. Understanding these causes aids in identifying at-risk individuals. Patel et al. (2024) list the risk factors for PDD in “Persistent Depressive Disorder,” published by StatPearls. Those risk factors include genetics, prior mental illness, trauma, life stressors and social determinants of health. The same review names greater childhood adversity, childhood loss of a parent and chronic depression in relatives as antecedents.
Treatment options for PDD include psychotherapy, particularly cognitive-behavioral therapy (CBT), medication such as antidepressants, and lifestyle changes that promote emotional well-being. Tailoring treatment to the individual’s needs is essential for effective management.
Preventive measures for PDD focus on maintaining mental health through regular physical activity, healthy eating, stress management techniques, and strong social support networks. Awareness and proactive measures reduce the risk of developing PDD.
The social implications of PDD are significant, affecting relationships, work performance, and overall quality of life. Understanding the disorder helps foster empathy and support from friends, family, and the community, encouraging those affected to seek help.
What is Persistent Depressive Disorder (PDD)?
Persistent Depressive Disorder (PDD), also known as dysthymia depressive disorder, is a form of depression characterized by a consistently low mood that lasts for an extended period. This condition is significant in the realm of mental health, as it severely impacts an individual’s ability to function in daily life, leading to considerable emotional distress and impairment.
In the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5), PDD is defined as experiencing a depressed mood for most of the day, more days than not, for at least two years in adults and one year in children and adolescents. The DSM-5 assigns PDD code 300.4, and the International Classification of Diseases, 10th Edition (ICD-10) uses F34.1.
Early-onset PDD refers to cases where symptoms begin before the age of 21. This form is particularly challenging, as it affects an individual’s development and coping strategies during formative years. While PDD is considered a type of depression, it is generally less severe than major depressive disorder (MDD) in terms of symptom intensity. However, due to its chronic nature, PDD leads to long-term functional impairment, making its impact significant over time.
Is Persistent Depressive Disorder a mood disorder?
Yes, Persistent Depressive Disorder (PDD) is classified as a mood disorder. An article published by Hopkins Medicine titled “Dysthymia” calls it a mood disorder that influences your mood, thoughts, and body.
As for its seriousness, PDD leads to substantial emotional distress and impairment in various aspects of life, making it a significant mental health concern.
Is Persistent Depressive Disorder a mental illness?
Yes, Persistent Depressive Disorder (PDD) is considered a mental illness. It involves a chronic, low mood that significantly affects daily functioning and overall quality of life.
PDD affects emotional regulation, cognition, and behavior, leading to symptoms such as fatigue, low self-esteem, and difficulty concentrating. As a chronic condition, it not only impacts mental health but also contributes to physical health issues, highlighting its seriousness as a mental illness that requires appropriate diagnosis and treatment.
Is Persistent Depressive Disorder a personality disorder?
No, Persistent Depressive Disorder (PDD) is not considered a personality disorder, but it co-occurs with personality disorders, particularly Borderline Personality Disorder (BPD).
PDD and personality disorders (PDs) co-occur, with a study published by Frontiers in 2021, suggesting the prevalence of comorbid PDs in PDD patients ranges from 51.2% to 70%. Regarding its seriousness, PDD causes considerable challenges, such as constant sadness, fatigue, and low self-esteem.
Which are the symptoms of Persistent Depressive Disorder?

The symptoms of PDD fall into physical symptoms, mental symptoms and signs that show up in children and teens. Mayo Clinic (2022), “Persistent depressive disorder,” lists the following:
- Physical symptoms: Tiredness and lack of energy, poor appetite or overeating, and sleep problems.
- Mental symptoms: Sadness, emptiness, loss of interest, low self-esteem, hopelessness, guilt, and trouble focusing or making decisions.
- Symptoms in children and teens: Depressed mood and irritability, which means easily becoming annoyed, impatient or angry.
How to Diagnose Persistent Depressive Disorder?
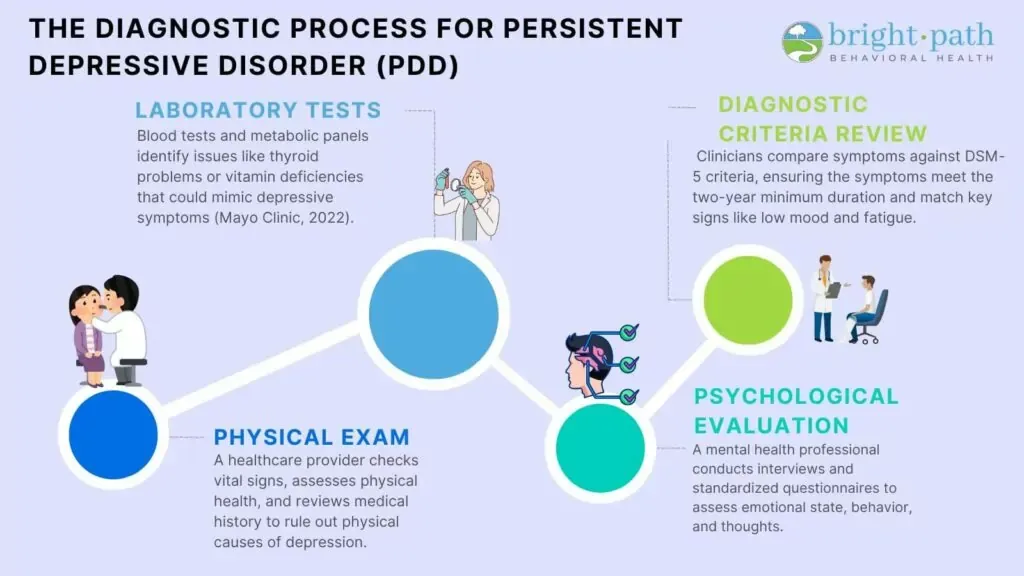
To diagnose PDD, you must conduct physical exams, laboratory tests, psychological evaluation, and diagnostic criteria review.
Patel et al. (2024) summarize the DSM-5-TR criteria in “Persistent Depressive Disorder,” published by StatPearls. The rule requires at least two of six symptoms alongside the long-lasting depressed mood. These are poor appetite or overeating, insomnia or hypersomnia, low energy or fatigue, and low self-esteem. The last two are poor concentration or difficulty making decisions, and feelings of hopelessness.
The 4 processes of diagnosing persistent depressive disorder are listed below:
- Physical Exam: A healthcare provider conducts a physical examination to assess overall health and rule out any medical conditions that contribute to depressive symptoms. This involves checking vital signs, evaluating physical health, and discussing medical history.
- Laboratory Tests: Blood tests and other lab evaluations identify root health issues, such as thyroid problems or vitamin deficiencies, that mimic depression. These tests help ensure that the symptoms are not due to a medical condition. Patel et al. (2024) list these tests in “Persistent Depressive Disorder,” published by StatPearls. The list includes a complete blood count, comprehensive metabolic panel, thyroid panel, vitamin B12 and folate. A urine toxicology screen also appears, with symptoms and patient history guiding any additional testing.
- Psychological Evaluation: A mental health professional conducts a thorough psychological assessment, which includes structured interviews and standardized questionnaires. This assessment focuses on the individual’s emotional state, behavior, and thoughts, helping to identify the presence and severity of depressive symptoms.
- Diagnostic Criteria Review: During the diagnostic criteria review, the clinician compares the individual’s symptoms against the criteria for PDD outlined in the DSM-5. This includes assessing the duration (at least two years in adults) and the specific symptoms experienced, such as low mood, fatigue, and difficulty concentrating. This thorough review ensures that the diagnosis is accurate and considers the individual’s unique experience.
How to know if you have dysthymia?
To know if you have dysthymia, self-assessment is an effective method of reflecting on your symptoms. While a formal diagnosis should be made by a mental health professional, these are some questions and tools to consider:
- Do you frequently feel sad, hopeless, or empty for most of the day?
- Have you experienced low energy or fatigue nearly every day?
- Do you struggle with feelings of worthlessness or excessive guilt?
- Have you lost interest in activities you once enjoyed?
- Are your sleep patterns disrupted, such as insomnia or oversleeping?
- Have you noticed significant changes in your appetite or weight?
Answering “yes” to several of these questions indicates that you are experiencing symptoms consistent with dysthymia. While low self-esteem contributes to feelings of sadness, it doesn’t necessarily indicate a depressive disorder.
The World Health Organisation (WHO) designed a depression self-assessment tool for individuals to evaluate their depressive symptoms. It inquires about any previous diagnoses of depression by a healthcare professional, any treatments received (both medication and non-medication), and specific symptoms like feelings of sadness, loss of interest, low energy, changes in appetite, and sleep disturbances. After answering the questions, a score is calculated to assess the severity of the symptoms.
When should you contact a medical professional for a PDD diagnosis?
Contact a medical professional for a PDD evaluation if you regularly feel depressed or low, or symptoms worsen. MedlinePlus (2026), “Persistent depressive disorder,” also advises calling for help right away when someone shows signs of suicide risk.
- Suicidal Thoughts or Self-Harm: Thoughts of harming yourself or considering suicide indicate a serious risk and require urgent intervention. It’s critical to seek immediate assistance in these situations.
- Severe Emotional Distress: Persistent feelings of hopelessness, worthlessness, or despair that disrupt your daily life are significant indicators that professional help is needed.
- Inability to Function: Symptoms that prevent you from carrying out daily responsibilities, such as work, school, or social interactions, make it important to consult a healthcare provider.
- Substance Abuse: Increasing reliance on alcohol or drugs to cope with feelings of depression worsens your condition and signals the need for professional support.
If you or someone you know is in crisis, call or text the 988 Suicide & Crisis Lifeline. You can also chat with the Lifeline at 988lifeline.org, and support is free, confidential and available 24/7.
Families in Wake County can also call the Alliance Health Crisis Line at 877-223-4617, which answers 24 hours a day. The Hope Center for Youth and Family Crisis in Fuquay-Varina offers 24/7 walk-in crisis care for young people ages 5 to 20.
For a diagnosis of Persistent Depressive Disorder, you should consult a primary care physician or a mental health professional.
Can a blood test detect dysthymia?
No, a blood test cannot directly detect dysthymia. Mayo Clinic (2022) covers diagnosis in its article “Persistent depressive disorder,” under Diagnosis and treatment. It explains that lab tests rule out other medical conditions that cause depressive symptoms, such as hypothyroidism.
A blood test is a medical procedure that involves drawing blood to analyze various components, such as hormones, nutrients, and other substances, to assess overall health.
Although blood tests help rule out underlying medical conditions that contribute to depressive symptoms (like thyroid problems or vitamin deficiencies), they do not diagnose mental health disorders like dysthymia.
What Causes Persistent Depressive Disorder?

The causes of PDD are negative thought patterns, family history, chronic stress, social isolation, and a host of other psychological, genetic, and environmental factors. According to an article published by Mount Sinai titled “Persistent Depressive Disorder,” common triggers of persistent depression are drug abuse, domestic abuse, family issues, and a loved one’s death.
Mayo Clinic (2022), “Persistent depressive disorder,” groups the common causes of Persistent Depressive Disorder as follows:
- Brain chemistry: Changes in neurotransmitters, the brain’s natural chemical messengers, play a large part in depression and its treatment.
- Inherited traits: PDD is more common in people whose blood relatives also have the condition.
- Life events: Traumatic events such as losing a loved one, money problems or high stress trigger PDD in some people.
By understanding these causes, individuals and healthcare providers have the opportunity to address the factors that contribute to Persistent Depressive Disorder and develop effective treatment strategies.
What are the risk factors of Persistent Depressive Disorder?
The major risk factors of PDD are a family history of depression, stressful life events and other mental health disorders. Mayo Clinic (2022), “Persistent depressive disorder,” also lists negative personality traits such as low self-esteem or harsh self-criticism.
- Chronic stress: Ongoing stressful life events or situations heighten the risk.
- History of other mental health disorders: Previous diagnoses of anxiety or other mood disorders contribute to the risk.
- Trauma or abuse: Experiencing trauma or emotional abuse during childhood or adulthood increases vulnerability.
- Social isolation: Lack of support networks or close relationships elevates the risk of developing PDD.
- Medical conditions: Chronic illnesses or conditions that affect physical health are also contributing factors.
How does filial piety impact Persistent Depressive Disorder?
Filial piety affects depressive symptoms in two opposite directions, depending on which form a teen experiences at home. Filial piety refers to the cultural value of respect and care for one’s parents and ancestors. Reciprocal filial piety protected Chinese adolescents against depressive symptoms, while authoritarian filial piety increased them through academic pressure.
The two main dimensions of filial piety are Reciprocal Filial Piety and Authoritarian Filial Piety, according to the 2021 research by Yingqiu Pan et al published in Frontiers in Psychology titled “The Effect of Filial Piety and Cognitive Development on the Development of Adolescents’ Depressive Symptoms: A Longitudinal Study.”
How do memory and cognitive factors impact Persistent Depressive Disorder?
Memory and cognitive factors significantly impact Persistent Depressive Disorder (PDD) by promoting negative thought patterns, impairing concentration and memory retention, and encouraging rumination on distressing thoughts.
Patel et al. (2024) review brain imaging research in “Persistent Depressive Disorder,” published by StatPearls. They report that brain imaging has reached no firm conclusions about brain structure or network function in PDD. The same review notes that the prefrontal cortex, anterior cingulate, amygdala and hippocampus have been implicated. Mars and Marwaha (2025), “Depressive Cognitive Disorders,” StatPearls, link amygdala and hippocampus changes in major depression to memory deficits.
How to treat Persistent Depressive Disorder?
To treat Persistent Depressive Disorder, combine medications, start therapy, and make lifestyle changes. Here’s an overview of the various treatment options:
- Talk therapy: Cleveland Clinic (2024), “Persistent Depressive Disorder,” lists cognitive behavioral therapy (CBT) as a core talk therapy for PDD.
- Medication: Mayo Clinic (2022) names SSRIs, tricyclic antidepressants and SNRIs as the antidepressants most commonly used for PDD.
- Combined treatment: Cleveland Clinic states that the most effective PDD treatment combines medications and talk therapy, or counseling.
- Lifestyle changes: MedlinePlus (2026) recommends enough sleep, a healthy diet, regular exercise and avoiding alcohol and drugs.
The 5 major factors affecting PDD treatment are individual variability, symptom severity, co-occurring disorders, support systems and treatment adherence.
- Individual Variability: Genetic predisposition and personal history influence treatment response.
- Severity of Symptoms: More severe cases require intensive treatment options.
- Co-occurring Disorders: The presence of anxiety or substance use disorders complicates treatment.
- Support Systems: Strong social networks enhance treatment effectiveness.
- Adherence to Treatment: Following prescribed medication and therapy regimens is crucial for successful outcomes.
By combining these various treatment options and tailoring them to individual needs, individuals with PDD effectively manage their symptoms and improve their quality of life.
What is the best treatment for Persistent Depressive Disorder?
The two best treatments for Persistent Depressive Disorder (PDD) are Medications and talk therapy, as stated in a 2022 study published by Mayo Clinic titled “Persistent Depressive Disorder”.
Talk Therapy is one of the most effective therapeutic approaches, helping individuals identify and change negative thought patterns. Medications on the other hand, particularly selective serotonin reuptake inhibitors (SSRIs), are commonly prescribed to help regulate mood. Combining these methods leads to better outcomes, as therapy addresses the emotional and cognitive aspects of PDD while medication helps manage biochemical imbalances.
What is the best medication for dysthymia?
The best medication for dysthymia is an antidepressant, chosen and monitored by a prescribing provider. Levkovitz et al. (2011) pooled placebo-controlled antidepressant trials for dysthymia in the Journal of Clinical Psychiatry. “Efficacy of antidepressants for dysthymia: a meta-analysis of placebo-controlled randomized trials” found a risk ratio of 1.75 versus placebo. Placebo response in dysthymia trials was 29.9%, compared with 37.9% in major depression trials.
Which antidepressant is best for dysthymia?
No single antidepressant is best for everyone with dysthymia, because side effects differ between the options. Harvard Health Publishing (2023), “Persistent depressive disorder (dysthymia),” reviewed by Stephanie Collier, MD, MPH, lists SSRIs such as fluoxetine first. The same article also recommends SNRIs such as venlafaxine, mirtazapine and bupropion for this disorder.
Can Persistent Depressive Disorder be cured?
Persistent Depressive Disorder is a chronic condition, yet many people recover fully with treatment. Medication, talk therapy, and lifestyle changes are ways to manage PDD and make one feel better. MedlinePlus (2026) describes the outlook for PDD in its article “Persistent depressive disorder.” It states that many people recover fully, while others continue to have some symptoms even with treatment.
How long does PDD last?
PDD lasts at least two years in adults and one year in teens, and some people keep symptoms for years. MedlinePlus (2026) describes PDD as a chronic condition in its article “Persistent depressive disorder.” The same source states that many people recover fully, while others keep some symptoms even with treatment.
The prognosis for PDD varies; with effective therapy and medication, many individuals experience significant symptom relief and improved functioning.
Factors influencing the duration and severity of PDD include the individual’s support system, the presence of co-occurring mental health issues, and overall life circumstances.
How to live with Persistent Depressive Disorder?
The different ways to cope with PDD include prioritizing sleep, maintaining a balanced diet, sticking to medication guidelines, incorporating regular exercise, etc. This finding was made by an article published by Medline Plus in 2022 titled “Persistent Depressive Disorder.”
- Prioritize Sleep: Aim for consistent and restorative sleep to help regulate mood and improve overall mental health.
- Stick to Medication Guidelines: Take prescribed medications as directed and communicate with your healthcare provider about any side effects to find the best treatment.
- Recognize Worsening Symptoms: Be mindful of early warning signs that indicate your PDD is worsening, and develop a proactive plan to address these changes.
- Incorporate Regular Exercise: Engage in physical activity regularly, as it boosts endorphins and improves mood.
- Engage in Enjoyable Activities: Find hobbies or activities that bring you joy and fulfillment, helping to counteract depressive feelings.
- Communicate Openly: Share your feelings with a trusted friend or family member to alleviate burdens and gain support.
- Surround Yourself with Positivity: Build a support network of caring and optimistic individuals who uplift and encourage you.
Is keeping busy a good strategy against dysthymia?
Yes, keeping busy is a beneficial strategy against dysthymia, as it helps distract individuals from negative thoughts and emotions. Engaging in productive activities promotes a sense of accomplishment and improves mood. However, it’s important to balance busyness with self-care and not use it as a way to avoid tackling underlying issues.
What are the possible complications of Persistent Depressive Disorder?
Persistent Depressive Disorder has 7 major complications, ranging from anxiety and substance misuse to suicidal thoughts. Mayo Clinic (2022), “Persistent depressive disorder,” links PDD with the following conditions:
- Anxiety and Other Mood Disorders: PDD is linked with anxiety disorders, other mood disorders and episodes of major depression.
- Suicidal Thoughts: PDD is linked with suicidal thoughts or behavior, which require immediate attention from a professional.
- Substance Misuse: PDD is linked with misuse of alcohol or drugs, which worsens mood and judgment over time.
- Relationship Difficulties: PDD is linked with relationship difficulties and family conflicts, according to the same Mayo Clinic list.
- School or Work Problems: PDD is linked with school or work problems and trouble getting things done.
- Chronic Pain and Illness: PDD is linked with continuing pain and general medical illnesses, which a physical exam checks for.
- Personality Disorders: PDD is linked with personality disorders and other mental health disorders, including borderline personality disorder.
Can dysthymia lead to major depression?
Yes, Dysthymia leads to major depression. Following a study by WebMD in 2023 titled “Double Depression”, over 50% of people with dysthymia will go on to develop a full-blown major depressive episode on top of their chronic dysthymia, resulting in “double depression.” This occurs when the chronic low mood characteristic of dysthymia intensifies, resulting in more severe symptoms typical of Major Depressive Disorder (MDD).
What is the difference between Persistent Depressive Disorder and Major Depressive Disorder?
Persistent Depressive Disorder (PDD) is a chronic form of depression lasting for at least two years, characterized by a consistent low mood and additional symptoms that are less severe but more enduring. Major Depressive Disorder (MDD), on the other hand, involves more intense depressive episodes lasting at least two weeks, with significant impairment in daily functioning. While PDD is long-lasting and less severe, MDD occurs in episodes and is typically more acute.
Can you have dysthymia and another disorder simultaneously?
Yes. It is possible to have dysthymia alongside other disorders, such as anxiety disorders, bipolar disorder, substance use disorders, and personality disorders.
Other simultaneous disorders include:
- Dysthymia and Major Depressive Disorder: Individuals experience both conditions simultaneously, a situation referred to as “double depression.” In this case, the chronic low mood of dysthymia intensifies into episodes of major depression, leading to more severe symptoms and significant impairment in daily functioning.
- Dysthymia and Bipolar Disorder: Dysthymia co-occurs with bipolar disorder, where an individual experiences persistent depressive symptoms during depressive episodes and also has manic or hypomanic episodes. This combination complicates treatment, as mood stabilization is crucial.
- Dysthymia and PTSD: People with dysthymia also have Post-Traumatic Stress Disorder (PTSD), particularly if they have experienced trauma. The chronic symptoms of dysthymia exacerbate the emotional distress associated with PTSD, requiring integrated therapeutic approaches to address both conditions effectively.
The same study by WebMD in 2023 titled “Double Depression”, noted that having both dysthymia and major depression at the same time complicates treatment. making comprehensive care essential.
Can dysthymia cause brain damage or fog?
Yes, dysthymia causes cognitive challenges such as brain fog, difficulty concentrating, remembering information, making decisions, and processing information quickly.
According to an article by Jennifer Huizen published in Medical News Today in 2023 titled “Brain fog and depression: What’s the link?”, the cognitive dysfunction associated with depression is thought to be caused by disruptions in the neural networks and neurotransmitter systems in the brain. Reductions in gray matter volume and white matter connectivity, as well as imbalances in neurotransmitters like serotonin and dopamine, lead to the cognitive symptoms of brain fog.
Can dysthymia lead to Alzheimer’s?
Yes, a history of depression is linked to a higher risk of developing Alzheimer’s disease later in life. Sáiz-Vázquez et al. (2021), “Depression as a Risk Factor for Alzheimer’s Disease: A Systematic Review of Longitudinal Meta-Analyses,” Journal of Clinical Medicine, found an odds ratio of 1.54.
Can dysthymia cause pain?
Yes, dysthymia is linked with physical pain, and Mayo Clinic lists continuing pain as a complication of PDD. Bair et al. (2003) reviewed studies of both conditions in “Depression and pain comorbidity: a literature review.” The review appeared in Archives of Internal Medicine and found the overlap runs in both directions. Pain is more common in people with depression, and depression is more common in people with pain.
Can dysthymia affect the health of an unborn child?
Yes, depression during pregnancy affects the health of an unborn child and the baby after birth. Jahan et al. (2021), “Untreated Depression During Pregnancy and Its Effect on Pregnancy Outcomes: A Systematic Review,” Cureus, linked maternal depression with preterm birth and low birth weight. The review adds that infants of depressed mothers “are more irritable, less active, and more likely to experience developmental delays.”
How to prevent Persistent Depressive Disorder?
To prevent PDD, you have to manage stress, reach out to family and friends for support, seek professional help, and set realistic goals. The ways to prevent PDD include:
- Reach Out for Support: Connect with family and friends for emotional support. Open communication helps alleviate feelings of isolation.
- Professional Help: Seek therapy or counseling early if experiencing symptoms of depression. Cognitive-behavioral therapy (CBT) is particularly effective.
- Limit Alcohol and Substance Use: Avoid excessive alcohol and drug use, as they worsen depressive symptoms.
- Establish Routine: Create a daily routine to provide structure and a sense of purpose, which improves mood and stability.
- Set Realistic Goals: Break tasks into manageable steps and set achievable goals to foster a sense of accomplishment and motivation.
What are the Social Aspects of Persistent Depressive Disorder?
The social aspects of PDD include awareness, insurance coverage, recognition as a disability, support networks, etc.
- Prevalence and Awareness: PDD is increasingly recognized within mental health discussions, yet many still underestimate its impact. Awareness campaigns aim to educate the public about the condition, helping to reduce stigma and promote understanding.
- Recognition as a Disability: PDD significantly impairs daily functioning, and its recognition as a disability varies by region and context. In some jurisdictions, individuals with PDD qualify for disability benefits, which provide crucial support.
- Insurance Coverage: Heboyan et al. (2021) studied state parity laws in Medical Care, using a national longitudinal sample of adolescents. Their paper is titled “Impact of Mental Health Insurance Legislation on Mental Health Treatment in a Longitudinal Sample of Adolescents.” They review earlier research and describe mixed evidence that parity laws change mental health treatment use. Some studies found modest increases in care for children, while others reported no changes in utilization.
- Support Networks: Social support plays a vital role in managing PDD. Community resources, support groups, and family involvement enhance treatment outcomes and provide individuals with a sense of belonging.
- Workplace Implications: PDD affects employment, with individuals facing challenges related to productivity and job retention. Employers are increasingly recognizing the importance of mental health support in the workplace, promoting healthier environments for affected individuals.
By exploring these social aspects, we understand the broader context of PDD and the need for systemic changes to support those affected.
How common is Persistent Depressive Disorder?
Persistent Depressive Disorder (PDD) impacts individuals of any age, although it is relatively rare compared to other mental health conditions. Cleveland Clinic (2024), “Persistent Depressive Disorder,” estimates that 1.5% of U.S. adults had PDD in the past year. The same source estimates that 2.5% of U.S. adults have experienced PDD at some time in their lives.
Furthermore, PDD is more commonly observed in women and among individuals who have relatives with the disorder; this indicates a potential genetic link.
Who does persistent depressive disorder affect?
Persistent Depressive Disorder (PDD) affects anyone, regardless of age or background. However, it is more prevalent in women and people with a family history of depression.
Are African Americans more prone to dysthymia?
Yes, African Americans and Mexican Americans had higher dysthymia rates than White Americans in a national survey. Riolo et al. (2005) published “Prevalence of depression by race/ethnicity: findings from the National Health and Nutrition Examination Survey III.” The American Journal of Public Health study surveyed 8449 people aged 15 to 40. Major depression was more common in White participants, while the opposite pattern held for dysthymic disorder.
Are men or women more affected by dysthymia?
Yes, women are more affected by dysthymia than men, according to several major medical sources. Cleveland Clinic (2024) reports in “Persistent Depressive Disorder” that the condition affects more women than men. Mayo Clinic’s article “Depression in women: Understanding the gender gap” covers depression in general rather than dysthymia. It reports that women are “nearly twice as likely as men to be diagnosed with depression.”
Factors that contribute to this disparity include hormonal fluctuations, social and cultural pressures, and higher rates of trauma and stress among women. Also, women are more likely to seek help for mental health issues, leading to higher reported cases.
Is Persistent Depressive Disorder a disability?
Yes, PDD Is considered a disability, particularly when it significantly impairs an individual’s ability to function in daily life. Under the Americans with Disabilities Act (ADA) and other disability regulations, mental health conditions that substantially limit major life activities qualify as disabilities.
For individuals with PDD, symptoms such as chronic low mood, fatigue, and difficulty concentrating affect work, social interactions, and overall quality of life. If PDD severely impacts daily functioning, it is eligible for accommodations or benefits related to disability support.
Does insurance cover Persistent Depressive Disorder?
Yes, insurance covers treatment for Persistent Depressive Disorder. Most health insurance plans, including those under the Affordable Care Act, provide coverage for mental health services, which include therapy, medication, and other treatments for PDD.
However, coverage specifics vary by plan, so people need to review their insurance benefits to understand what services are included, any copays or deductibles, and whether a referral is needed for specialized care. Seeking treatment is essential for managing symptoms and improving quality of life.
How to help someone with Persistent Depressive Disorder?
To help someone with Persistent Depressive Disorder (PDD), offer emotional support by listening without judgment and encouraging them to express their feelings. Be patient and understanding, as PDD affects their mood and behavior. Encourage them to seek professional help if they haven’t already, and offer to assist with finding resources or accompanying them to appointments. Help them maintain a routine by suggesting activities they once enjoyed and engaging in social interactions. Lastly, educate yourself about PDD to better understand their experience and provide meaningful support.


Clinically reviewed by Dr. Shantel Sullivan, Ed.D., LCSW, Chief Executive Officer